Multi-Location Practice AI Rollout Sequencing
Sequencing AI rollouts site-by-site prevents costly failures across your portfolio.
Multi-location medical groups do not fail at AI rollouts because the technology underperforms. They fail because the environment itself resists a single configuration working everywhere at once, and the sequencing decisions that would prevent that failure rarely get made deliberately.
The hardest environment to sequence an AI rollout in
Every location in a multi-site group carries its own combination of payer mix, EHR setup, provider schedules, and staff habits. An agent configuration built around how one clinic handles a particular payer portal or a particular exception in the EHR will not simply drop into site two and work the same way. For portfolio operators, private equity-backed groups and management services organizations chief among them, this problem compounds further: acquired practices typically arrive with their own legacy processes, inconsistent documentation habits, and no shared operational baseline to build from. The appeal of deploying everywhere at once makes sense on a spreadsheet, since group-level ROI projections look larger when every site goes live together. But the groups that have captured the fastest actual returns did not move that way. They moved one workflow, one site at a time, and let each deployment inform the next.
Administrative AI as the right starting layer
The returns available to multi-location practices right now sit almost entirely in administrative and revenue cycle work, for structural reasons. Clinical AI carries a separate set of obstacles: provider liability, trust gaps among clinicians, and reimbursement uncertainty that administrative workflows simply do not face. Clinical AI converts to full deployment at roughly half the rate of administrative AI, held back by those same unresolved questions. That leaves administrative automation as the layer where sequencing decisions are both immediately actionable and immediately consequential: the framework in this piece applies to scheduling, prior authorization, claims, and the rest of the administrative stack, while clinical AI remains a separate conversation with its own governance process and its own timeline.
The logic behind starting with a single pilot site rather than rolling out across all locations at once
One pilot site lets a group validate an agent's configuration, surface the integration quirks that only appear in production, and measure workflow-specific results before any of those variables multiply across the rest of the portfolio. The decisions made at that first site, how the agent navigates a specific payer portal, how it handles exceptions in a particular EHR layout, which cases it hands off to a person rather than resolving on its own, become the template every later site works from. That matters because errors caught at one location are fixable. The same errors appearing simultaneously across ten locations turn into rework at scale, and they erode staff confidence in the system before it has had a chance to prove anything. Bessemer and Bain's Healthcare AI ROI Scorecard found that providers and pharma companies are furthest along in pushing to deploy piloted, vetted solutions at scale, while payers are still at the ideation stage. Pilot-then-scale is not a cautious fallback; it is the structure the most advanced operators are already converging on. Picking the pilot site itself deserves the same discipline: the right choice is the site that produces the cleanest signal, meaning stable volume, workflows that are already reasonably consistent, and staff willing to engage with a new process.
What workflow to automate first
Once the pilot site is chosen, the workflow selected for it should be the one with the highest volume, the clearest rules governing it, and the most consistent execution across staff already. Those three traits determine how reliable the agent will be and how quickly its impact becomes visible. High volume gives the agent enough repetitions to surface its edge cases fast and enough throughput to produce a measurable result inside the first review window. Clear rules mean the agent's decision logic can be specified precisely, which lowers the odds of a consequential error and makes its performance easy to audit. Consistent execution means the practice is automating something with a known baseline, so improvement gets measured against a real number. In most multi-location practices, three workflows meet all three conditions: prior authorization, claims denial management, and inbound scheduling. Prior authorization is high-volume and governed by payer policy that rarely changes mid-stream, which makes it a natural candidate; CMS-0057-F already mandates FHIR-based Prior Authorization APIs be live by January 1, 2027, which gives groups a regulatory clock to plan around. Claims denial management follows a similar logic: an agent categorizes the denial reason, determines the corrective step, and either resubmits automatically or routes the claim to a person, a decision tree that maps cleanly onto agent architecture. Inbound scheduling earns its place where call abandonment and access delays are the real bottleneck, since an agent handling intake, matching patients to the right clinician and location, and managing reschedules directly reduces abandonment and no-show numbers. None of the three sits above the others as a universal first choice. The workflow causing the most daily frustration is not automatically the right one to start with, especially if it depends heavily on unstructured judgment calls rather than fixed rules, because that variability will produce inconsistent agent behavior and a result too murky to act on. The right first workflow is whichever of the three matches the practice's actual bottleneck, selected against the volume, rules, and consistency criteria.
Designing an agent configuration that travels across locations without breaking
The configurations that expand across locations without needing to be rebuilt share one trait: centralized decision logic with location-specific parameters sitting on top of it, rather than a separate, independently built agent for every site. For a scheduling agent, that means one system that holds each location's hours, providers, policies, and insurance panels as data. Separate instances per site turn every new acquisition into its own maintenance project. For payer portal work, the agent needs to handle every portal the group actually touches, not just the dominant payer, because when a group works across many different payer portals each week, any interface change breaks automation scripted around a fixed path. Agents that read a portal's layout visually, the way a staff member reads a screen, hold up better than ones scripted to follow a predetermined sequence of clicks. This is the core advantage of computer-use agents in a multi-location setting: they interact with EHRs, payer portals, and other software by reading the screen and navigating it the way a person would, without requiring an API integration built to a fixed spec. Because no two sites look identical on the back end, an agent that adapts to what is on screen holds up better than one that requires the screen to match a predetermined integration. Exception handling needs the same centralized treatment. The rules for when a task exceeds the agent's confidence and needs a human should be identical across every site, both for compliance reasons and because inconsistent escalation behavior is where agent errors start to compound. The pilot site's configuration, exceptions and all, becomes the template, and bringing on the next site becomes a matter of adjusting parameters.
Pilot-window metrics for declaring readiness to expand
Expansion should happen because the numbers say it is time. A deployment can look smooth day to day and still be falling short on the one metric that actually matters for that workflow. The right metrics differ by workflow. For prior authorization, the signals are first-pass approval rate, average turnaround time, and how often cases get escalated to a person; an agent clearing a high share of authorizations on the first pass with few escalations is ready to move to the next site, while one generating frequent escalations needs more configuration work first. For claims, the signals are the denial rate on agent-submitted claims compared with the pre-automation baseline, how fast the resubmission cycle runs, and how often claims get routed to human review; the target is a denial rate at or below baseline paired with a materially shorter cycle time. Bessemer and Bain's survey found that buyers realized ROI in roughly half the time they had projected, with ROI arriving in about 12 months against a projected 24. That result belongs to deployments that measured the right things from the start, rather than ones that rolled out broadly and hoped aggregate savings would show up later. Thirty days at the pilot site is the floor for a measurement window, and workflows with higher downstream stakes, prior authorization and claims chief among them, call for a longer look before anyone moves to expand. Staff feedback deserves equal weight alongside the metrics, treated as a leading signal. If staff are quietly routing around the agent or redoing its work by hand, the configuration is already failing, well before the KPIs catch up to show it. A simple channel for that feedback belongs in the pilot from day one.
The order and pace for bringing additional locations online
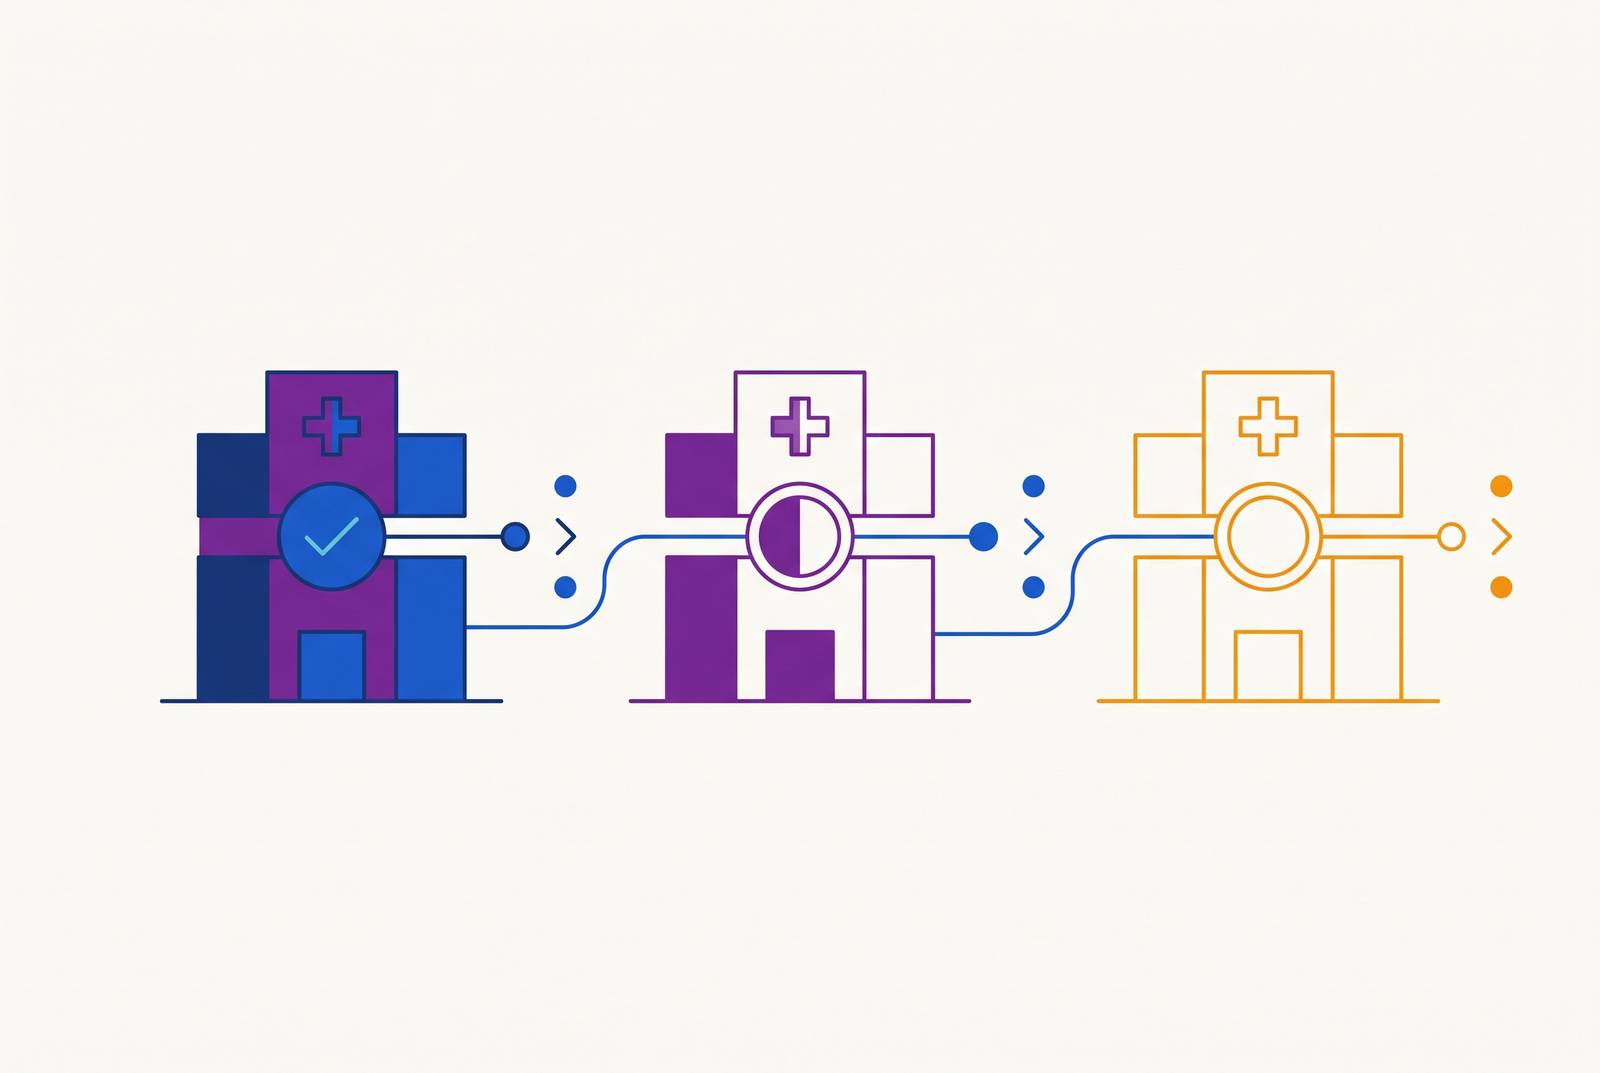
Once the pilot configuration clears its KPIs, the sequence of expansion follows operational similarity to the pilot site, not org-chart hierarchy and not which location happens to be largest. A site with a materially different payer mix, or a specialty with its own prior authorization volume the pilot never saw, is a second pilot, with its own configuration and its own measurement window, before it can serve as a template for sites like it. The pacing that works is wave-based: a defined group of similar sites goes live together, followed by a stabilization period before the next group starts, which keeps the ability to course-correct intact rather than letting one misconfiguration cascade across the entire portfolio at once. For PE and MSO operators with acquisitions arriving on an ongoing basis, this sequence belongs inside the integration playbook itself. A newly acquired practice enters at the start of the sequence, configure, pilot, measure, expand, rather than getting dropped in at the tail end of a rollout that is already mid-flight.
Compliance and security in the sequencing plan
HIPAA compliance and data security are not a box to check before the pilot launches. They are a constraint that needs validating at every stage of the rollout, because the surface area exposed to protected health information grows with each new site and each new workflow added. Every agent that touches PHI, whether it is reading an EHR screen, navigating a payer portal, or processing a scheduling request, needs a Business Associate Agreement with the vendor, and that holds at every site and every workflow, not only at the first deployment. As the rollout expands, so does the attack surface: more sites mean more login credentials, more network touchpoints, and more staff interacting with whatever the agent produces, each one a potential point of exposure if it is not governed the same way everywhere. SOC 2 Type II certification from the vendor is the baseline assurance that security controls are in place and have been audited, and practices should confirm that status again before expanding, not just once at the time they first chose the vendor. Expansion phases create a specific risk: staff at sites not yet live sometimes turn to consumer AI tools to approximate what the deployed agent does elsewhere, a practice sometimes called shadow AI. A clear policy on which AI tools are approved, communicated before each wave goes live, closes that gap. None of this scales linearly if the architecture is centralized to begin with: one configuration with consistent exception routing and audit logging is far easier to govern than a collection of site-specific builds, which is one more reason the centralized design described earlier matters.
Sequencing workflows within a single site after the first deployment succeeds
Once the first workflow is running reliably at the pilot site, choosing the next one follows the same logic used the first time: highest volume, most rules-governed, most consistent, applied now to whatever administrative burden remains at that site. The better move is finishing one workflow completely, across the EHR, the payer portals, and every other system staff touch, before introducing a second one. Depth at a single site beats breadth before the first workflow is fully running. Revenue cycle management, if it was not the first workflow chosen, is usually the strongest second choice: an agent that verifies eligibility ahead of a visit, checks codes against payer rules, flags claims at risk of denial, and drafts appeals when claims are rejected touches the entire revenue cycle. McKinsey's analysis of AI in the revenue cycle identifies this kind of end-to-end orchestration as capable of driving a substantial reduction in cost to collect and faster cash realization. Cancellation recovery and new-patient referral scheduling make strong candidates for a second or third workflow at sites where provider utilization is the binding constraint, since both are high-volume, rules-governed, and measurable directly against how full the schedule stays. Workflows that depend on more than one agent working together, a prior authorization that triggers a scheduling confirmation once approved, for instance, should wait until each component workflow is stable on its own, since combining two workflows before either is proven just compounds whatever errors either one still has.
The repeatable pattern that emerges once the framework is applied once
Groups that have run this sequence once, one workflow, one site, measured against real KPIs, with a configuration proven before it expands by similarity, find that every deployment after the first moves faster. The decision logic is already known, and the configuration itself has already been tested in production. The second site goes live faster than the first because exception handling is already defined. The third workflow gets configured faster than the first because the agent's way of working with the EHR and the payer portals is already mapped out. For PE and MSO operators absorbing new acquisitions on an ongoing basis, this sequence becomes a standing part of the integration process itself: each newly acquired practice enters the same path, starting with its highest-volume standardized workflow at one site, and the return compounds across every location that follows the same pattern. Bessemer and Bain's survey found that healthcare AI ROI arrived roughly twice as fast as buyers had projected, exceeding expectations in about 40 percent of use cases. The groups capturing that return are the ones that have gotten agents running in measurable, real work and are extending what already works to the next site and the next workflow, rather than the ones still running parallel pilots across their entire portfolio at once. Success in this framework is measured by whether each deployed agent performs like a trained staff member available around the clock, against the KPIs the group agreed to before deployment started, at every site in the portfolio that follows.